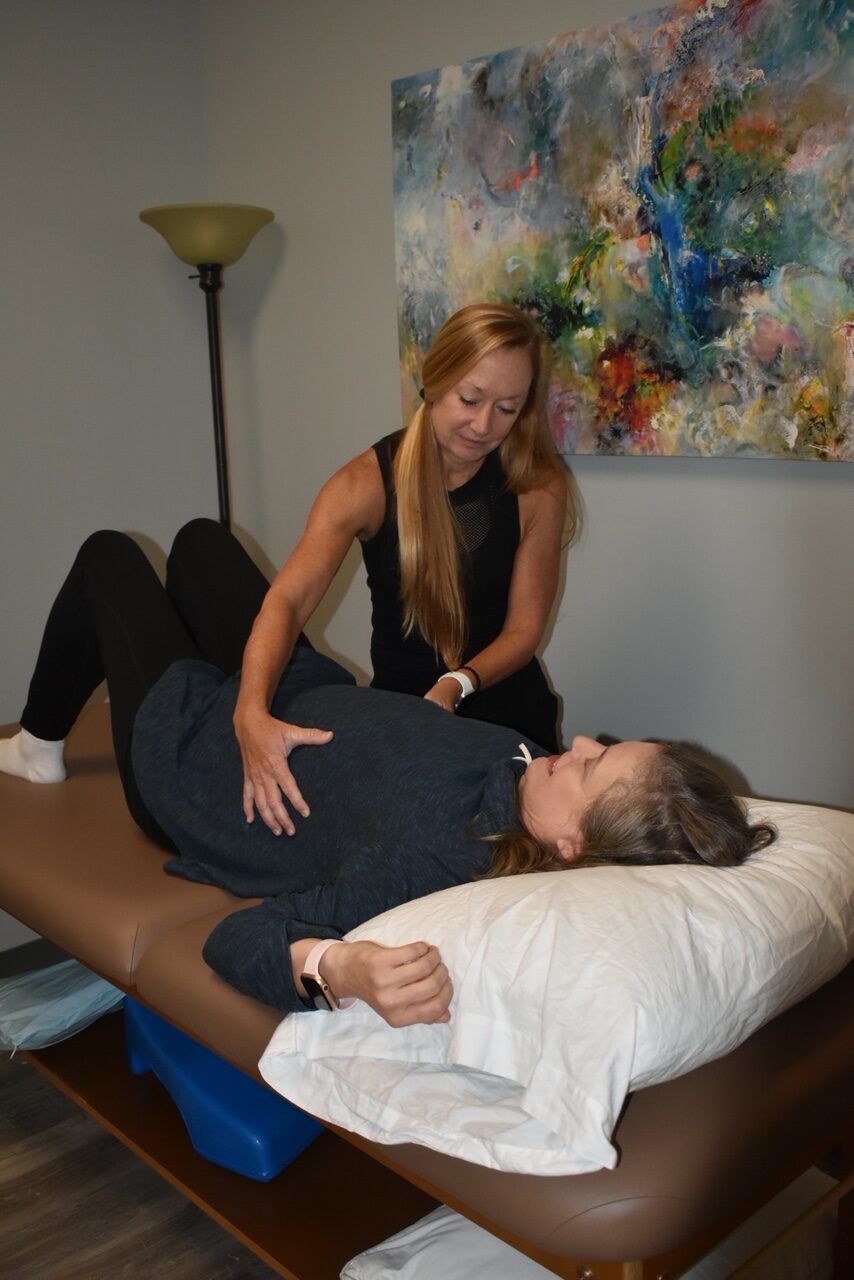
What is a good Pelvic Floor PT session like? (evaluation) 

Considering that pelvic floor physical therapy is becoming more “normalized” , it is important for patients, clinicians, and physical therapists to understand what a quality physical therapy session is like.  Here is our best answer to  “what is a good pelvic floor PT session like?”
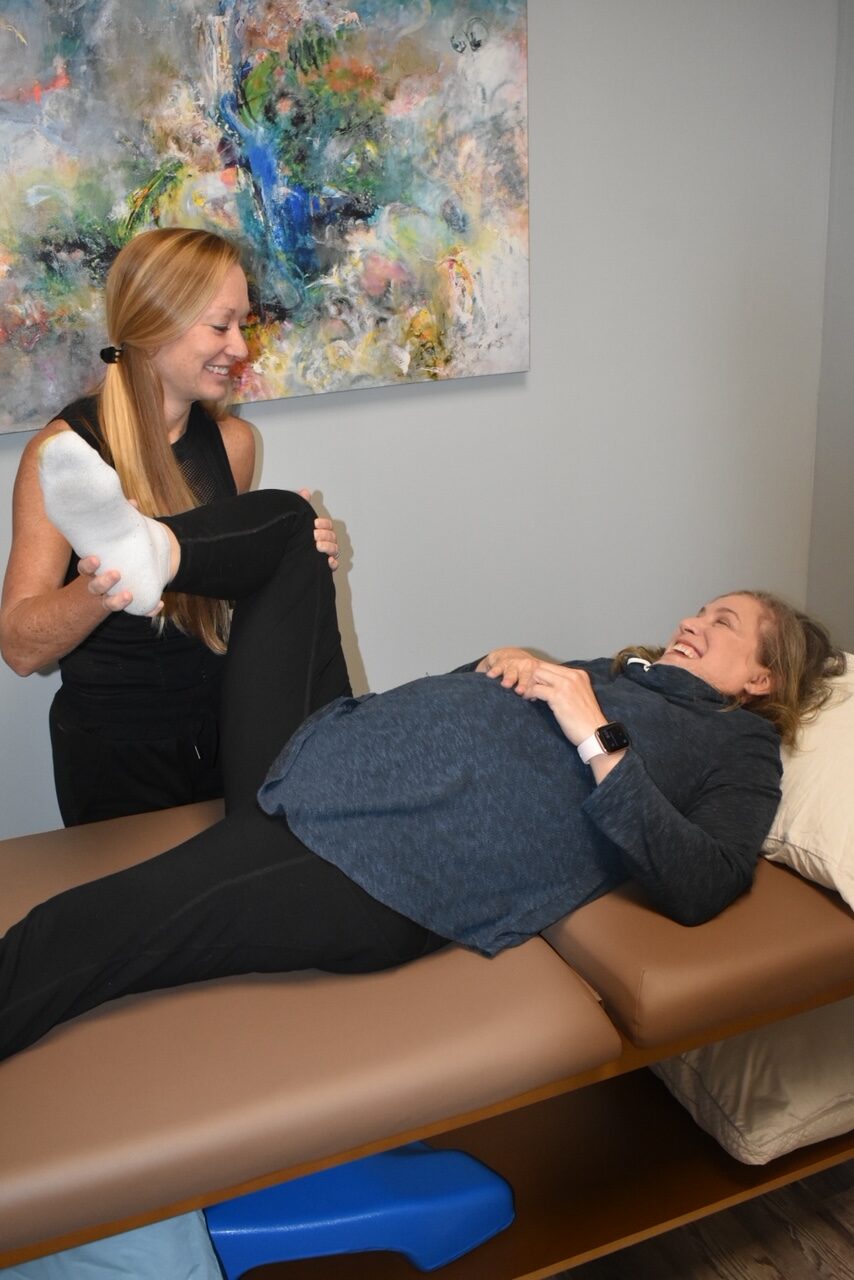
Evaluation Appointment

The evaluation appointment should last at least 60 minutes and the goal is to figure out what the main contributing factors are to the patient’s symptoms. PTs act like investigators uncovering all of the potential reasons for why the patient might be experiencing pelvic pain, urinary urgency, painful sex, incontinence, constipation, prolapse, etc.  

Below are some questions that you will likely be asked:

  • When did your symptoms start?
  • What exacerbates your symptoms?
  • What alleviates your symptoms?
  • How often do you urinate during the day? Do you have urge, leakage, nocturia?
  • How often do you have a bowel movement and do you strain?
  • Do you have pain with intercourse?
  • What activities do your symptoms limit?
  • What kind of work do you do?
  • What doctors/other PTs have you seen?
  • Have you had any diagnostic procedures done?
  • What past treatments have you had?
  • What medications are you taking?
  • How has this problem impacted your life?
  • Have you stopped participating in things you enjoy because of this problem?
  • What is your diet like?
  • What fluids do you drink?
  • How is your sleep?

The interview portion helps us to see the “big picture” and develop a hypothesis as to why the pelvic floor dysfunction may exist. The interview also allows us to gain the necessary information to know what is of MOST concern to the patient. If there are many areas of dysfunction and concern, it may take several visits to evaluate all structures. 

The examination consists of a visual exam looking at posture, alignment, and movement patterns followed by manual palpation of external structures. External areas to be examined may include the abdomen, inner thighs, hips, the bony pelvis. We are looking for trigger points, tight muscles, joint dysfunction, symmetry or asymmetry between right and left sides, connective tissue dysfunction, and even visceral motility/ mobility. Through this testing, we are looking for a reproduction of familiar pain to the patient so that the patient can best be treated. 

A key aspect that sets pelvic floor physical therapists apart from other physical therapists is our training in an internal pelvic floor muscle (PFM) exam. This exam is typically performed transvaginally in females and transrectally in males. A  transrectal exam in our female patients may be indicated as well. During the internal PFM exam we are evaluating for muscle tone, trigger points, strength, prolapse, and motor control.  Also, we are looking for any irritability in the peripheral nerves of the pelvis, and vaginal and anal tissue integrity.

At the end of the appointment, findings are reviewed with the patient. It is important to us that our patients understand what we found and how we plan on treating the symptoms. In addition, if we find that further evaluation is necessary by someone out of our scope of practice, or a referral is needed to another provider to supplement Pelvic Floor PT, we will refer the patient to a trusted provider. During the evaluation session, the patient is given a few exercises or lifestyle modifications to start to perform on their own. 

Assessment

The assessment is an important part of the evaluation process. This is where we consider our patient’s history and how various factors could have led to the development of the impairments that we believe are primary sources of pain and/or dysfunction. This is an ongoing process that happens during each appointment as things evolve. The assessment allows us to effectively develop short and long-term goals which help guide an efficient and effective treatment plan.

Short term and long term goals

When we are first evaluating the patient about their history we ask what their goals are for physical therapy. Everyone’s goals are different and it is our job to help them achieve them. Typically the duration of a  physical therapy treatment plan can last between a few weeks to several months, or longer, depending on the severity of the situation. We use short incremental goals to justify our treatments and collectively achieving the short term goals results in achieving the patient’s long term goals.

Are you ready to get started with Pelvic Floor Physical Therapy? Contact us!

Magic City Physical Therapy 
3075 John Hawkins Parkway, suite J
Hoover, AL 35244
Phone (205) 202-0874
Fax (205) 293-3895
www.magiccitypt.com
@magiccitypt (Instagram and Facebook)

Elimination Diet for Interstitial Cystitis

Many people with Interstitial Cystitis (IC) find that diet changes and an elimination diet are great tools to manage IC’s frustrating ups and downs. Soon after starting an IC diet, most people find that certain foods are worse for their bladder than others. While the IC diet lists many foods to avoid, IC patients often find that some foods on the list they can enjoy without much harm to their bladder.

Dietary Differences 

Why do we have these individual dietary differences? One answer may be that IC is a disease with many different subsets. Different subsets of IC patients may have different causative factors for their bladder symptoms and this leads to differing experiences with food. Factors in food sensitivity may be due to the presence of “Hunner’s Ulcers” and the number of years one has had the disease.

Another possible explanation for individual differences may be food intolerances or allergies. These food reactions may affect the bladder through the mechanism of bladder mast cells. In other words, the irritating food substances pass through a “leaky” intestinal lining and get into the blood stream, where they travel to a sensitive organ, and cause a painful reaction there. One could reasonably speculate that perhaps an IC bladder, already irritated and sensitized from other causes, may provide a target organ for this process in an allergic IC patient. Many IC patients also have something called irritable bowel syndrome (IBS), a gastrointestinal condition that has also been linked to mast cells and increased intestinal permeability. Data from several studies have suggested that allergic reactions to food antigens may be a factor for some IBS patients.

Finding the Offending Foods 

Whatever the medical reasons for our dietary problems and differences, patients want as much control over bladder symptoms as possible. This can be done by pinpointing which foods provoke the bladder. Typical pin-prick allergy testing can reveal false positives and false negatives. What’s more, reliable tests for reactions to food additives (ie., monosodium glutamate or MSG) have yet to be developed. Known as RAST tests, ELISA tests, or cytotoxic tests, these blood tests for food allergies are now available through allergists. If you have food allergies, this kind of test can not only pinpoint foods your body reacts to immediately, but can also identify foods that cause delayed reactions. Reliability of these tests has increased over the years. Finding and eliminating food allergens may be helpful in controlling your particular bladder symptoms.

Food intolerances are not the same as food allergies. An intolerance is a general term that means you get negative symptoms when you eat a particular food. Intolerances are not the same as allergies. Your bladder may react to foods, but that reaction may not involve an allergic process.Doctors consider food allergy tests inappropriate or useless for diagnosing food intolerance problems that are not allergies. The tried-and-true and cheapest method for discovering if foods cause symptoms, remains the elimination diet. It will uncover which foods cause you trouble regardless of the underlying mechanism.

General Guidelines for Elimination Diets 

Most elimination diets have two phases. In the first phase, foods are eliminated and symptoms will be reduced (if successful). In the second phase, foods are gradually reintroduced while watching for the appearance of symptoms. The whole process may take months to complete. Nutritional adequacy needs to be paid attention to during these manipulations to your diet. Throughout the time you are manipulating your diet, it is important to keep a symptom diary. Because many IC patients also have migraine headaches, irritable bowel syndrome, fibromyalgia, and other medical conditions, it is important to take note of the effect of diet on all symptoms.

There are several kinds of elimination diets, and each person must evaluate for themselves which one is best suited for their particular situation. It is also a good idea to check with your doctor or consult a registered dietitian before embarking on any long-term dietary modifications. This is especially true if you have other serious medical conditions besides IC.

There is some evidence that true food allergies can be “outgrown” by children and that adults who modify their diet may lose their reactivity over time. This is in contrast to evidence that some IC patients’ food sensitivities may get worse with time. The biggest thing to remember with the IC Diet and Elimination Diet is that all patients are different; patients need to figure out what works best for them for reducing IC symptoms. Diagnostic tools such as an elimination diet can help IC patients with sensitive bladders figure out which foods bother them and help those patients gain better control of their symptoms.

Do you need help managing your IC Symptoms? Pelvic Floor Physical Therapy can greatly help. Contact us for more information!

Magic City Physical Therapy 

Hoover, AL 

www.magiccitypt.com

Instagram @magiccitypt 

Phone (205)202-0874 

Fax (205)573-3709

Can Pelvic Floor Dysfunction Be Causing My Low Back Pain?

https://www.youtube.com/watch?v=a3ewxs6QnIQ

Low back pain (LBP) is a condition of pain to the lumbar spine with or without symptoms radiating down the legs. The link between LBP and pelvic floor dysfunction (PFD), particularly in women, is becoming more evident in research. Pelvic floor dysfunction (PFD) occurs when the muscles that comprise the pelvic floor become uncoordinated which can adversely cause urinary urge, frequency, or incontinence, pelvic organ prolapse, constipation, pain with sex, and/or bowel incontinence. Uncoordination of the pelvic floor muscles may mean they have poor strength and endurance, increased tension, shortened length, and overactivity. Pelvic floor muscles have attachments from the groin muscles, deep abdominal muscles, and spinal muscles, all of which need to be coordinated as well. The diaphragm, transversus abdominis, PFM, and multifidus work together to influence posture through intra-abdominal pressure regulation and thoracolumbar fascial tension. Current evidence shows that individuals with low back pain have a significant decrease in pelvic floor function compared to individuals without low back pain.

Low back pain (LBP) is one of the most common musculoskeletal conditions. Approximately 70-80% of the population will experience at least one episode of LBP during their lifetime. Some causes of LBP include trauma, disease, and poor postural habits. Over 25% of all women experience PFD. The true prevalence of PFD is underestimated due to lack of standardized definitions and under-reported symptoms. PFD also involves psychosocial implications that can greatly affect the patient’s quality of life. PFD does not typically have one specific cause. The development of PFD most likely involves many components.

The major risk factors for PFD are pregnany/childbirth, hormonal changes, obesity, pelvic surgery, hip or tailbone injury, high stress, abnormal posture, among others. A longitudinal study on younger, middle-age and older women reported that women with pre-existing incontinence, gastrointestinal problems, and breathing disorders were more likely to develop LBP than women without these problems. This can be the result of abnormal postural activity of the trunk muscles including muscles of respiration and continence which provide support to the spine and pelvis.

The pelvic floor forms the inferior border of the abdominal-pelvic cavity. It supports the abdominal-pelvic organs and the PFM are the only transverse load-bearing muscle group in the body. These muscles function as a unit instead of separately contracting. They play an important role in maintaining and decreasing intra-abdominal pressure during functional tasks such as lifting, sneezing, coughing, and laughing to prevent bladder and bowel incontinence. The PFM, along with the deep abdominals and multifidus, help to stabilize the trunk and control intra-abdominal pressure in response to movement.
If you have LBP and PFD, Pelvic Floor Physical Therapy can help. Find a therapist who takes a thorough history and clears any red flags. Find a therapist who evaluates not just the Pelvic Floor internally, but assesses the entire body. Posture should be evaluated as well as strength and range of motion of the feet, knees, hips, and spine. Lifestyle habits should be discussed including diet, sleep, exercise, and sexual habits.

How do you know if you have Pelvic Floor Dysfunction? If you can answer YES to any of these questions, you would benefit from an evaluation by a Pelvic Floor Physical Therapist.

●  Do you urinate more than 6-8 times during daytime hours?
●  Do you ever have urine leakage during activities such as coughing, sneezing, laughing, or exercise?
●  Do you ever have urine leakage associated with sudden strong urge?
●   Do you have trouble reaching the toilet in time?
●  Have you ever lost bowel control?
●  Do you have pain with sex?
●  Do you get up to urinate during the middle of the night?

Do you have Pelvic Floor Dysfunction and/or Low Back Pain? Contact us to schedule a thorough evaluation and get started on the right track to improving your Pelvic Health!

Magic City Physical Therapy
Hoover, AL

www.magiccitypt.com

Instagram @magiccitypt
Phone (205)202-0874
Fax (205)573-3709

Sources:

Eliasson K, Elfving B, Nordgren B, Mattsson E. Urinary incontinence in women with low back pain. Manual Therapy. June 2008;13(3):206-212.


Dufour S, Vandyken B, Forget MJ, Vandyken C. Association between lumbopelvic pain and pelvic floor dysfunction in women: A cross sectional study. Musculoskeletal Science and Practice. 2018 Apr 1;34:47-53.


Nygaard I, Barber MD, Burgio KL, Kenton K, Meikle S, Schaffer J, Spino C, Whitehead WE, Wu J, Brody DJ, Pelvic Floor Disorders Network. Prevalence of symptomatic pelvic floor disorders in US women. Jama. 2008 Sep 17;300(11):1311-6.


Arab AM, Behbahani RB, Lorestani L, Azari A. Assessment of pelvic floor muscle function in women with and without low back pain using transabdominal ultrasound. Manual therapy. 2010 Jun 1;15(3):235-9.

The Pelvic Floor and Hip Connection

https://youtube.com/shorts/rT5SCRFzBz0?feature=share

Your hip rotators, which move your hip in and out, have direct connections to the pelvic floor. What happens at the hip can affect what happens at the pelvic floor and vice versa. Hip strength and mobility is key to a healthy pelvic floor! The position of your hips can also influence what position your pelvic floor is in. For example, a hip in external rotation (knees wide) puts the pelvic floor stretch but helps it descend. A hip in internal rotation (ankles wide) makes the pelvic floor engage and lift. Oftentimes hip pain and
pelvic floor dysfunction exist together. For example, you may be experiencing hip pain and also have urinary leakage. You might have hip pain and also suffer from pain with sex.

The Obturator Internus is one of six external rotators of your hip. The role of the obturator internus (OI) muscle is to assist in rotation and stabilization of the hip on the pelvis. This provides stability while moving as well as a site of attachment for the pelvic floor muscles. . In addition to the OI’s role in mobility, the muscle is a pathway for the pudendal nerve and blood vessels as it works its way through the pelvis.

If the OI becomes strained, tight or weak you may experience pain in the outside of the hip, near the sitting bone or deep inside the pelvis in a place that may seem hard to reach. It may refer pain to your lower abdomen or groin.
Moreso, due to the close relationship of the OI with the pelvic floor muscles you may also experience painful sitting, urinary urgency and frequency, urinary leakage, and/or sexual dysfunction. OI-related symptoms are not limited to one gender over another, or sedentary individuals versus athletes.

The pudendal nerve and the OI also share space in the pelvic cavity. The PN branches off in three directions as it leaves the pelvic cavity to innervate the rectum, vaginal/perineal region and the genitals, and one of the pathways it travels through is in the region of the OI muscle and fascia. Changes in hip mechanics, muscle tissue, strength or coordination may contribute to pelvic symptoms if this affects the route of the pudendal nerve (PN) through the obturator muscle and fascia. If a nerve is compressed, stretched, or irritated you may feel different sensations in the pelvis that are typical of nerve involvement in other areas of the body. Normal symptoms in the pelvis of PN compromise may include numbness, pain, burning, aching, or itching in the rectum, vaginal or perineal regions, and/
or in the penis or clitorial region.

Restoring mobility and function of the OI, pelvic floor, and other hip muscles can help to resolve your literal pain in the buttocks and get you back to running, biking, traveling, sexual activities and all of the other fun things you have stopped with due to pain or other symptoms.

If you have these symptoms or have not succeeded with traditional orthopedic physical therapy for your hip, contact us to learn more about how pelvic floor physical therapy can restore your muscle function and get you back to all of your activities!

Check this video out to see if you can SMOOTHLY move your hips in and out of rotation equally. If not, contact us for a hip and pelvic floor assessment!

Magic City Physical Therapy
Hoover, AL

www.magiccitypt.com

Instagram @magiccitypt
Phone (205)202-0874
Fax (205)573-3709